Oncology target expression profiling in large FFPE cohorts

Confirm your nominated target is expressed in the right compartment, prevalent across patients and tumor types, and characterize its distribution across normal tissues.

We profile expression at cohort scale with the spatial resolution bulk readouts miss — backed by 150+ validated IHC and mIF panels.

Recent papers based on IHC/mIF panels

Cancer Cell journal logoClinical cancer research journal logoScience Advances logoCancer Cell journal logoSignal transduction and targeted therapy journal logoNature cancer journal logoCell Reports Medicine journal logoMed a Cell Press journalCell Reports Medicine journal logoJournal of Hematology & Oncology

WHAT target profiling answers

From a nominated target to a go/no-go decision

Once a target has been nominated, tissue-level expression profiling answers the four questions that support program decisions:
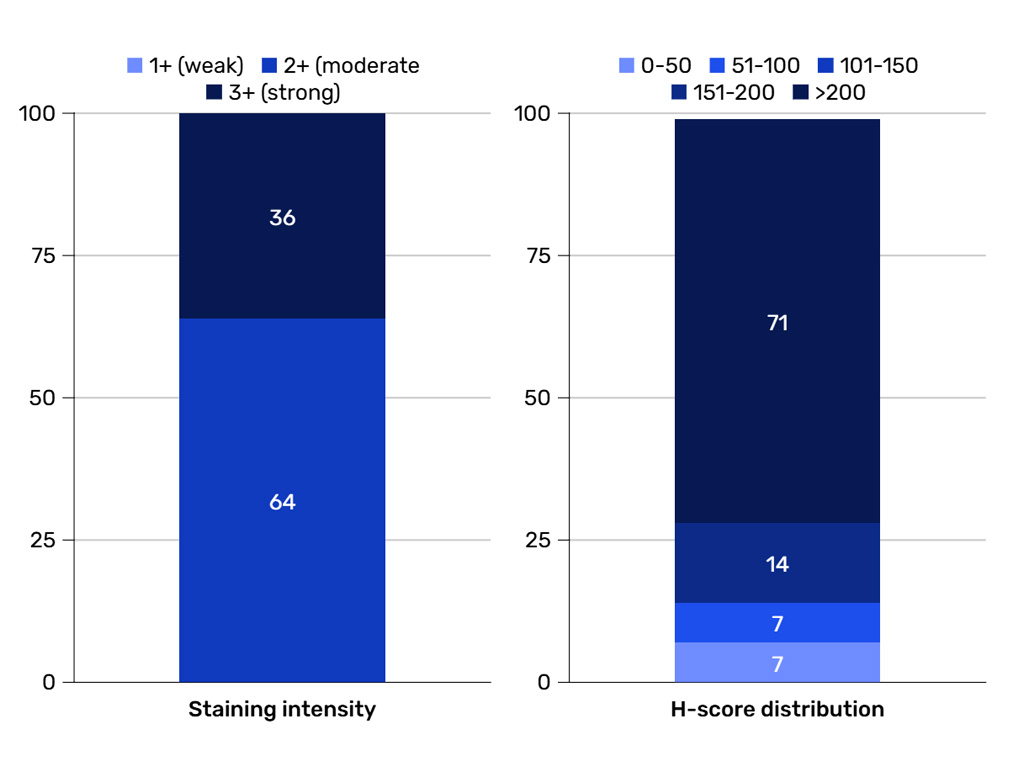
cancer target prevalence ffpe tissues staining intensity H-score

Target prevalence at scale

What fraction of patients are target-positive within a tumor type and across histologies or molecular subtypes?
oncology target localization compartment specificity CRO services

Protein localization and compartment specificity

Is the target on the cell membrane, in the cytoplasm, or in the nucleus? Restricted to tumor cells or also present in stromal/immune compartments?
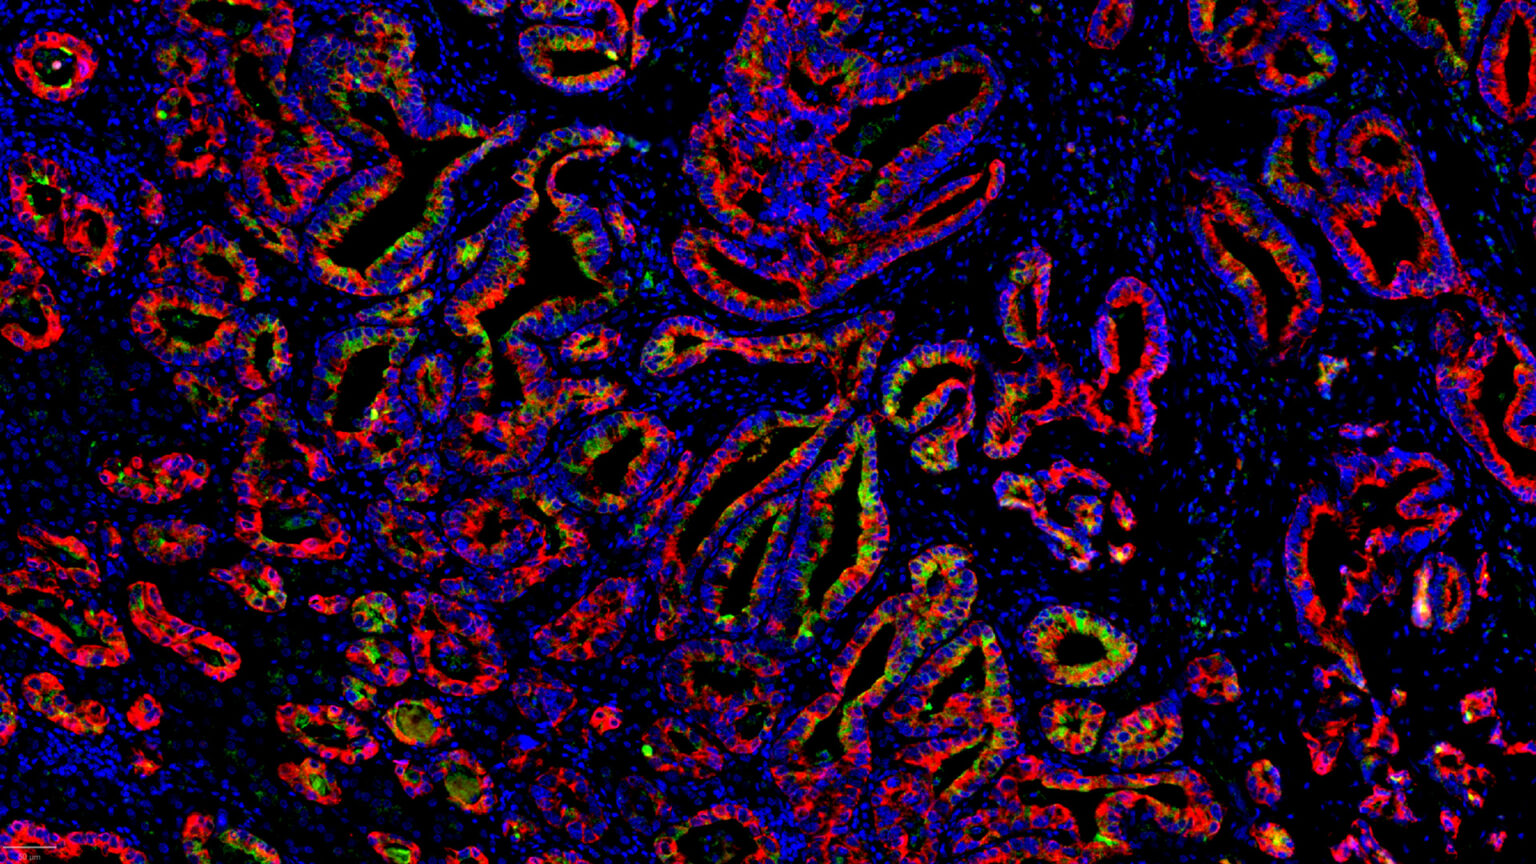
Immunofluorescence staining of oncology target CLDN18.2 (green) in human lung cancer sample (panCK in red)

Spatial context within the tumor

Is expression homogeneous or heterogeneous, clustered in discrete foci? Is it associated with proximity to specific cell types or microenvironmental niches?
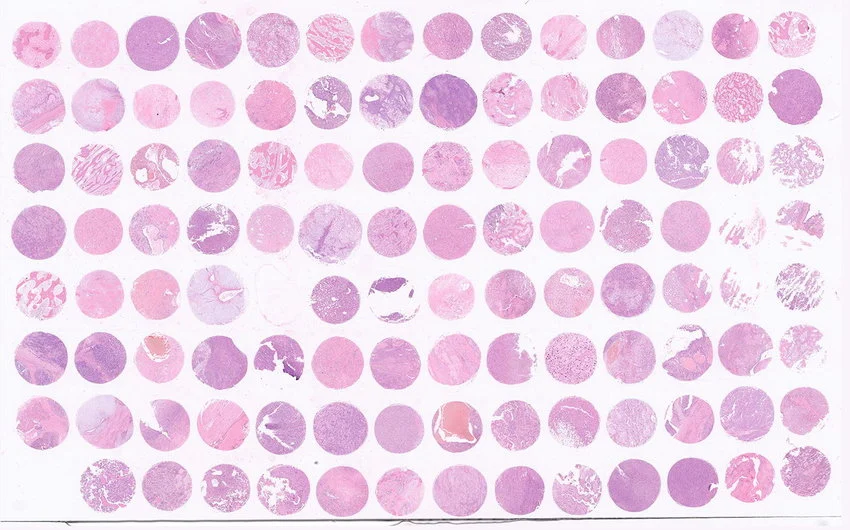
FFPE normal tissue sourcing

Target expression in normal tissues

Is the target expressed in healthy tissues, informing on-target/off-tumor toxicity risk?

Discuss your target discovery project

Our 4-step workflow

From study design to defensible target expression evidence

Study design & FFPE tissue sourcing

The right cohort to answer your target question

Each project is scoped with a PhD-level study director to align cohort, panel, and format with your target and constraints. We leverage 150+ validated IHC/mIF TME markers and source FFPE specimens through regulatory-compliant biobanks.

Key outputs

  • FFPE cohort design: sample numbers, inclusion criteria, controls, normal tissue selection
  • Panel strategy: antibody selection and panel design (singleplex or multiplex)
  • Fit-for-purpose format: TMA for cost-efficient screening, whole-slide for heterogeneity and spatial context
  • Early de-risking: assay validation and pilot study before scaling
About FFPE sourcing

Sample QC & processing

Reproducibility you can defend in due diligence

Every specimen passes through a controlled QC and processing workflow before staining and analysis — designed to minimize batch effects, and ensure reproducibility across cohort-scale studies.

Key outputs

  • Secure intake with unique IDs and chain-of-custody documentation
  • Pathology suitability review (e.g. tumor content, ROI definition)
  • In-house sectioning with harmonized thickness and labeling
  • Managed storage conditions for blocks and slides

Automated staining & high-throughput imaging

Cohort-scale data with controlled, reproducible workflows

Automated staining and high-capacity whole-slide digitization deliver fast, reproducible target expression data at scale. Operating an ISO-certified quality management system, our built-in controls and QC ensure signal integrity from slide to dataset.

Key outputs

  • Automated IHC and mIF staining on 2 Ventana Discovery platforms
  • Whole-slide and TMA digitization on 2 PhenoImager HT systems
  • Run-level controls and imaging QC on every batch
  • ISO 9001 / ISO 13485 certified quality management system
Explore our digital pathology platform

AI-assisted image analysis & biostatistics

Quantitative evidence on prevalence, compartment, and normal tissue

Our in-house data science team turns whole-slide images into quantitative, decision-ready datasets — backed by expert pathologist review, integrated biostatistics, and transparent deliverables ready to share with partners.

Key outputs

  • AI-assisted segmentation and scoring (membrane, cytoplasmic, nuclear; tumor vs. stroma vs. immune compartments)
  • Spatial analysis (cell density, distance, neighborhood, architecture)
  • Biostatistics: prevalence estimates, subgroup comparisons, cutoff exploration, clinical metadata integration
  • Per-sample tables, cohort summary figures, annotated images, and methods/QC appendix
More about image & data analysis
Discuss your target expression project

TARGET VALIDATION CASE STUDIES

Target expression profiling in practice
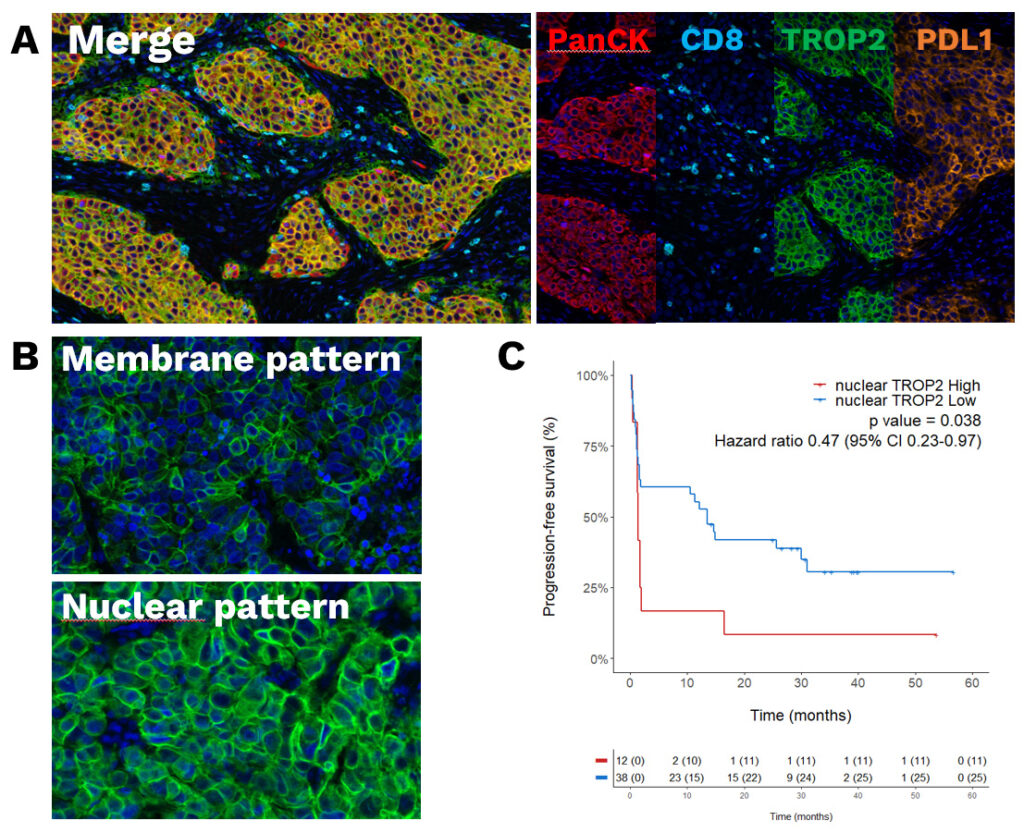
Spatial localization changes the target’s clinical story

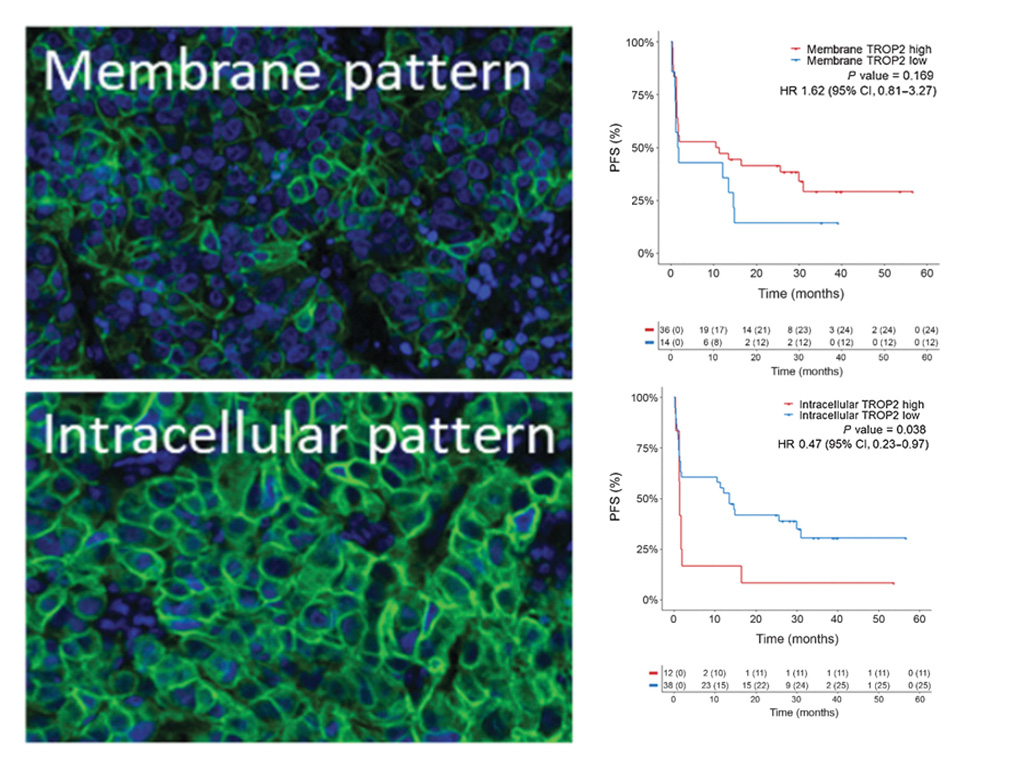
How nuclear vs. membrane TROP2 distribution predicted immunotherapy response in 50 NSCLC patients — published in Clinical Cancer Research, 2024.

The question: TROP2 is a clinically validated ADC target in NSCLC. But does total TROP2 expression — the standard IHC readout — capture everything that matters? Or does subcellular localization carry information that bulk scoring misses?

The strategy: Multiplex immunofluorescence panel (TROP2 + CD8 + PanCK + PD-L1 + DAPI) on FFPE tumor sections from 50 patients with advanced NSCLC treated with immune checkpoint inhibitors. AI-assisted quantification of TROP2 distribution across subcellular compartments, validated by expert pathologist review.

The finding: Nuclear TROP2 localization — not captured by conventional total-expression scoring — stratified patients into distinct response groups. Patients with high nuclear TROP2 showed significantly worse progression-free survival on anti-PD-(L)1 therapy than patients with predominantly membrane-localized TROP2.

What it shows: Total target expression alone can miss biologically relevant differences in subcellular localization. In this NSCLC cohort, nuclear TROP2 was associated with poorer outcomes on anti-PD-(L)1 therapy, illustrating how spatially resolved protein profiling can distinguish membrane-accessible target expression from intracellular localization and refine target assessment for therapeutic development.

TROP2 target expression profiling NSCLC CRO services explicyte
The Explicyte team at their Bordeaux laboratory

Paul Marteau, PharmD (study director), Imane Nafia, PhD (CSO), Loïc Cerf, MSc (COO), Alban Bessede, PhD (founder, CEO), Jean-Philippe Guégan, PhD (CTO)

Contact our team

Discuss your target expression project and request a quote

Whether you start from a nominated target, an existing IHC reagent, or a specific indication, we can design the right expression study and define next steps. Within 3 business days, a PhD-level study director will reach out to discuss your project, propose the right panel and cohort strategy, and provide pricing.

Explicyte (Bordeaux, France) uses your details to respond to your request. Privacy policy

Answers about target expression profiling

Frequently asked questions

What is target expression profiling, and when is it needed?

Target expression profiling confirms whether a nominated oncology target is expressed in the right tumor compartment, at meaningful prevalence, and and characterizes its distribution across critical normal tissues. It’s the de-risking step between target nomination — often from transcriptomic screening — and downstream development decisions on indication choice, modality fit, and toxicity risk. We use IHC and multiplex IF on FFPE tissues at cohort scale, with AI-assisted image analysis and expert pathologist review.

IHC is the right choice for high-throughput screening of small number of targets across large cohorts — fast, cost-efficient, and supported by clinical and regulatory familiarity. Multiplex IF is the right choice when you need to see the target in context — co-expression with markers like CD8, PD-L1, PanCK, or stromal markers, or when subcellular localization and spatial relationships matter for the program decision. Many programs use both: IHC for prevalence screening, multiplex IF for mechanistic and contextual confirmation.

TMA (tissue microarray) is the right format for cost-efficient screening across many patients — well-suited to prevalence studies, indication exploration, and normal tissue expression panels. Whole-slide imaging is the right format when heterogeneity, spatial context, or invasive margin biology matters for the program decision. We can also combine the two: TMA for cohort screening, whole-slide on selected cases for deeper characterization.

We profile target expression in panels of critical normal tissues — selected based on your target’s biology, the modality you’re developing, and known toxicity-relevant organs. Normal tissue panels can include broad multi-organ coverage or be custom-designed around the target biology, therapeutic modality and specific safety hypotheses. Outputs include per-tissue scoring, representative annotated images, and an interpretation of normal-tissue expression findings and their potential relevance to on-target/off-tumor risk.

A typical study includes: a scoping discussion with a PhD-level study director, written proposal with options and pricing, FFPE cohort design (or sourcing through accredited French biobanks), panel design and pilot validation, automated staining and scanning, AI-assisted image analysis with expert pathologist review, biostatistical interpretation, and a final report with raw data, ready-to-use figures, and a written discussion. Most studies complete in 8 to 14 weeks depending on cohort size and panel complexity.

Explicyte integrates the key components of target expression profiling within a single oncology-focused workflow: access to clinically annotated FFPE cohorts, a library of 150+ validated IHC and multiplex IF markers, automated staining and imaging within an ISO 9001 / ISO 13485-certified quality framework for tissue biomarker analysis, and in-house AI-assisted image analysis combined with expert pathologist review. Our data science team also integrates expression data with clinical and molecular metadata to support prevalence estimates, subgroup analyses and program-level decisions. This expertise is supported by peer-reviewed publications across oncology and immuno-oncology.

Both. Sponsors can ship FFPE blocks or slides from their own cohort, biobank partner, or clinical trial collection — we handle intake, QC, and processing under our quality framework. For sponsors who need cohort access, we source clinically annotated FFPE specimens through regulatory-compliant biobanks. Many projects combine both: sponsor-provided clinical samples plus sourced normal tissue panels.

Reproducibility is built in at four layers. Sample QC and standardized processing minimize pre-analytical variability. Automated staining (Ventana Discovery platforms) with controlled run conditions and built-in controls ensures batch-to-batch consistency. Imaging QC validates signal integrity before analysis. Run-level controls and an ISO-certified quality management system ensure data is traceable and defensible for partner due diligence or regulatory review.

Yes. Our data science team integrates expression results with clinical variables (treatment history, response, survival), molecular subtypes, and other -omics datasets when available. Outputs include subgroup analyses, prevalence estimates by clinical strata, association statistics with outcomes, and visualizations ready for internal review or external partner discussions.

After target expression profiling, the next step depends on your decision points. If localization or normal tissue expression raises questions, deeper characterization with spatial transcriptomics (Xenium, Visium HD, Atera) can resolve them at gene-level resolution. If the target validates and a functional question emerges, our preclinical immuno-oncology platform supports efficacy and mechanism-of-action studies with cell-based assays and patient-derived 3D models. We can design the full validation roadmap with you during scoping.

Explicyte Oncology CRO logo

Capabilities

Modalities